

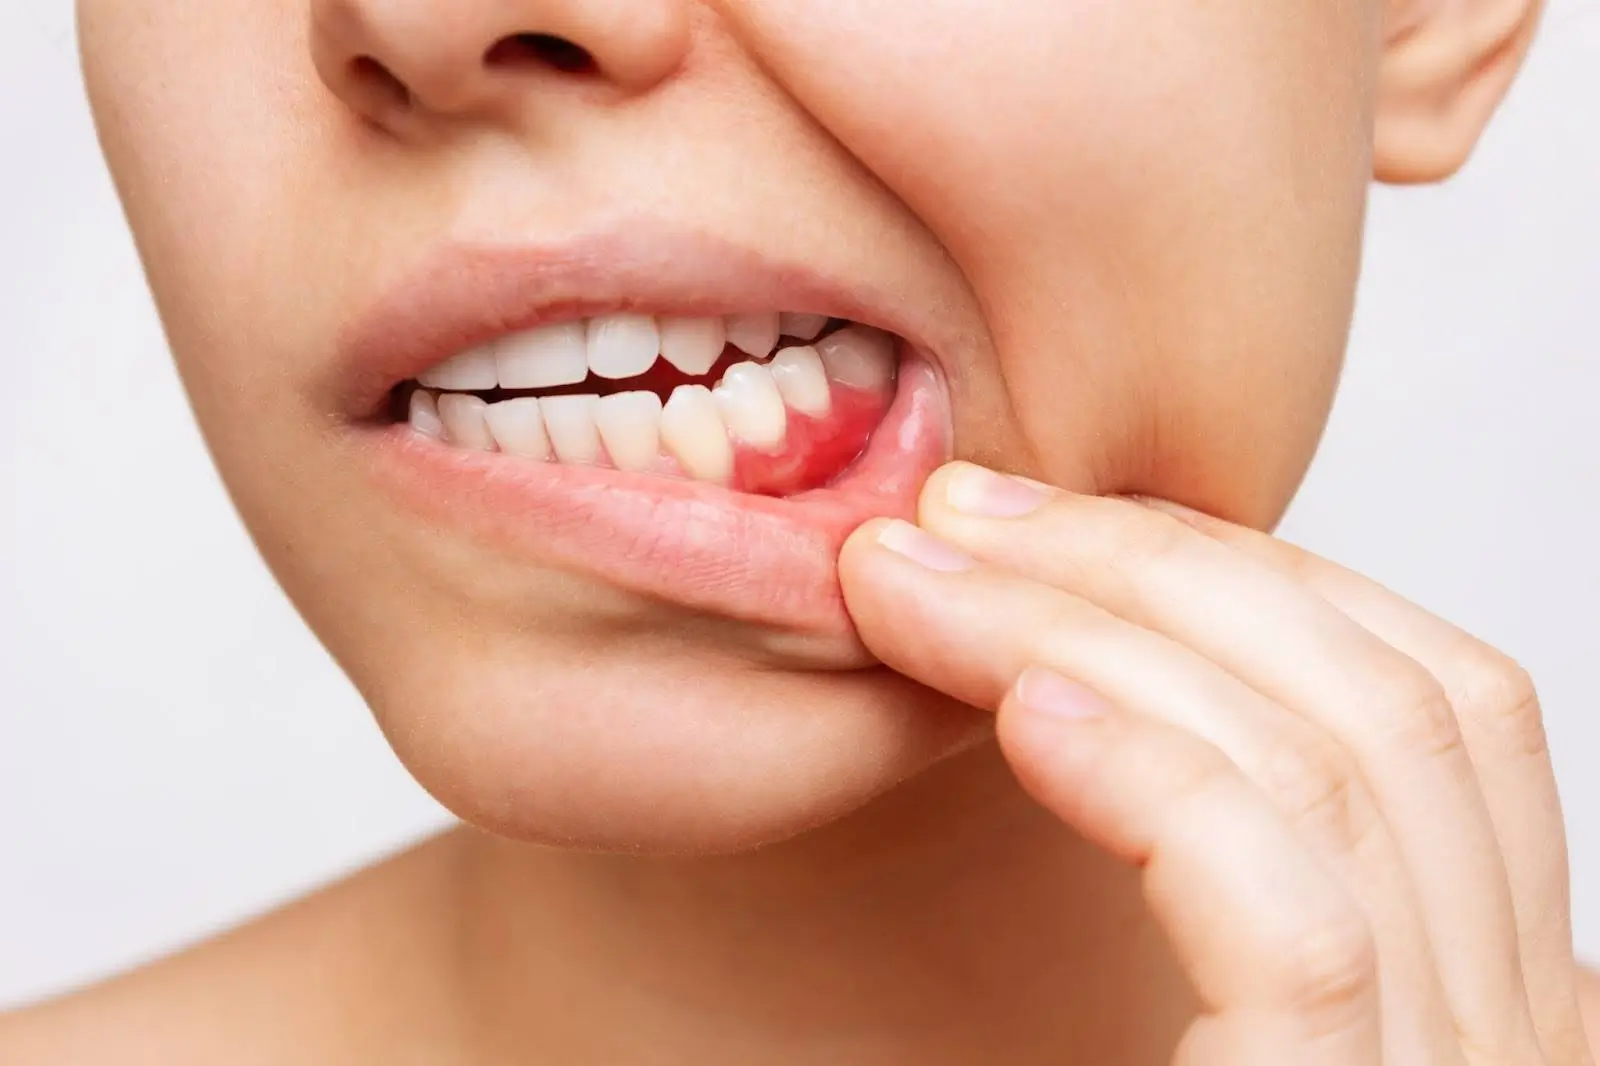
In most cases, yes. A history of gum disease does not stop you being a candidate for dental implants, and a great many of the patients we place implants for lost their teeth to periodontal disease in the first place. Most people considering dental implants after periodontal treatment go on to qualify for dental implants once the infection is controlled.
What you cannot do is place a dental implant into an active infection. Gum disease has to be brought under control first, and depending on how much damage has already been done, the bone may need rebuilding before an implant has anything to hold onto. That sequence is the whole answer, and everything below explains what it involves.
Why Active Gum Disease And Implants Do Not Mix
Periodontal disease is an infection of the gums and the bone beneath them, spreading below the gum line and destroying the attachment that holds teeth in place. Gum disease is the leading cause of tooth loss in adults, and untreated gum disease is what separates a mouth that can support implants from one that cannot.
A dental implant relies on the same foundation a natural tooth does. Implants are placed into the jaw, and healthy bone and gum tissue grow tightly around the implant site. Put one into a mouth where an active infection is dissolving bone, and the infection reaches your new implant as readily as it reached the tooth it replaced. The risk of implant failure in an untreated mouth is not a small statistical difference. It is the most predictable reason implants will fail early.
So the answer to “can I get implants with gum disease” is really an answer about timing. Not never. Not yet.
What Disqualifies You From Getting Dental Implants?
Very little permanently stops anyone being able to get a dental implant. It is worth separating what genuinely rules out a dental implant procedure from what only delays it.
Delays treatment, does not prevent it:
- Active gum disease, until it is treated and stable enough for dental implant placement
- Insufficient bone, until it is grafted or an alternative approach is planned
- Uncontrolled diabetes, until blood sugar is managed
- Smoking, which we will discuss honestly rather than issue as an ultimatum
- Recent radiation to the jaw, depending on dose and timing
Requires genuine caution:
- Certain bone medications, particularly intravenous bisphosphonates
- Severe uncontrolled medical conditions affecting healing
- An unwillingness to maintain the result, which matters more here than in almost any other treatment
A patient with a history of gum disease has demonstrated susceptibility to it, and past gum disease raises the risk of developing gum disease again around new implants. Dental implants do not remove that susceptibility, and the maintenance schedule afterwards is not optional.
Treating Gum Disease Before Implants
Gum disease treatments vary enormously with how far the disease has progressed and how far the disease impacts the bone, which is why a proper assessment comes before any implant plan. The disease must be treated first either way, but how we treat gum disease depends entirely on what that assessment finds. Treating the gum tissue and stabilising the bone beneath it is one job, not two.
We measure pocket depths around every tooth, take X-rays and usually a CBCT scan, and map the bone structure at each site: where the gums and bone have already gone, and how much bone and gum tissue remains. Only then can anyone tell you whether dental implants are realistic and on what timeline. We review your full medical and dental history at the same appointment.
Gingivitis, the earliest form of gum disease, often responds to scaling and root planing, which removes plaque and tartar from below the gum line and lets the tissue reattach. Many patients need nothing more.
Periodontitis, the advanced form of gum disease, may need pocket reduction surgery to reach deposits that cannot be cleaned any other way, or laser therapy where it suits the case. Where the supporting structure has been lost, regenerative procedures can rebuild some of it.
Teeth beyond saving are better removed than defended. A tooth held by little bone is a reservoir of infection sitting next to the site where an implant needs to go. Extracting it and preserving the socket at the same appointment often produces a better result than years of trying to hold on.
Our page on periodontal disease treatment covers these procedures in more detail.
How Long Do You Wait Between Treatment And Implants?
Usually a few months, though it varies more than patients expect.
After non-surgical therapy we re-measure at around six to eight weeks. If pockets have closed, bleeding has stopped and the tissue is firm, we have the gum disease under control and dental implant planning can begin. That is what tells us the disease is being treated successfully rather than merely held at bay. After surgical treatment, allow three to six months for the tissue to mature.
Where extractions and grafting are involved, the graft sets the schedule rather than the gum treatment: a socket preservation graft is typically ready in three to four months, larger reconstruction in four to six.
What we will not do is start the implant clock on a mouth that has been treated but not re-checked. Stable means measured, not assumed.

What If Gum Disease Has Already Caused Bone Loss?
This is the situation most people asking this question are actually in, and it is the reason so many are told dental implants are not possible for them.
Periodontal disease destroys bone. By the time teeth are lost due to gum disease, the ridge is often narrow, short, or both, and significant bone loss can leave too little to support an implant. But that changes the plan rather than ending it. The question is whether there is enough to support an implant now, or whether we rebuild first.
Depending on what remains, we may rebuild the site with a bone graft before placing the implant, or work with the bone you still have and let the remaining ridge support the implant. Shorter and narrower implants, implants angled to engage denser bone away from the damaged area, and full-arch protocols designed around posterior bone loss all avoid extensive grafting in the right case.
Implants in the upper back jaw are the usual sticking point, because that is where the sinus and periodontal loss compound each other. Being told the bone is inadequate is often a statement about one approach rather than about you. It is worth a second opinion before accepting that implants are off the table.
Can You Get All-On-4 Dental Implants With Gum Disease?
Frequently, and for patients with advanced periodontal disease it is often the better answer rather than a compromise. It is the one situation where gum disease and dental implants work with each other rather than against each other.
Where disease has affected most of the remaining teeth, treating each one individually can mean years of procedures to preserve teeth that will not survive the decade. A full-arch approach removes the compromised teeth, eliminates the infection with them, and places implants into the areas of bone that remain sound — usually toward the front of the jaw, where periodontal loss tends to be least severe.
There is a real advantage here that is rarely stated: taking out the diseased teeth removes the bacterial reservoir entirely. Patients who have battled periodontal disease for years often find maintenance considerably simpler afterwards.
It is not automatically right. It depends on how many teeth are genuinely beyond saving and what bone remains. But if you have been quoted an endless sequence of periodontal procedures, ask whether a full-arch approach would serve you better.
Does Gum Disease Go Away Once You Have Implants?
No, and this misconception causes real harm.
Dental implants cannot decay, which leads people to assume they are immune to everything. They are not. Does gum disease affect dental implants? It does, differently from the way it affects natural teeth, but it does: the tissue around your implant can become infected much as it does around a natural tooth. It has its own name — peri-implantitis — and the strongest predictor of developing it is a history of periodontal disease. Gum disease causes bone loss around implants just as it does around teeth, and the disease can cause an implant to be lost if nobody catches it.
Nor does removing the affected teeth cure the condition. Periodontal disease is driven by the bacteria in your mouth and how your immune system responds to them, and neither changes because some teeth were replaced. What changes is that the most heavily infected sites are gone, which makes the remaining problem far more manageable.
The honest position: implants are an excellent solution for patients who have lost teeth to gum disease, and they require more diligence from those patients than from anyone else.
Peri-Implantitis: Gum Disease Around Implants
Watch for bleeding around your dental implant when you brush, gums that look red or puffy rather than firm and pale pink, soreness, a bad taste, or any hint of the implant feeling different.
Caught at the early stage, when only soft tissue is inflamed, it usually resolves with professional cleaning and better technique at home. Once bone is being lost around the implant it becomes considerably harder to treat, and the implant can be lost.
The distinction matters because the early warning sign is easy to dismiss. Bleeding around the implant is never normal. Report it rather than waiting for your next scheduled visit.
Keeping Implants Healthy After Gum Disease
If you have a history of periodontal disease, the maintenance that follows dental implant surgery is what determines how long your implants last. Protecting gum health is what keeps gums and implants stable together, and the aim is to prevent gum disease returning rather than to treat it again.
- More frequent professional cleaning. Three or four visits a year rather than two, at least initially. This is the single most effective thing.
- Cleaning between the teeth every day. Floss, interdental brushes or a water flosser, whichever you will actually use consistently.
- Not smoking. It restricts blood supply to the gum tissue and is the clearest modifiable risk factor for both gum disease and implant failure.
- Managing diabetes, which is bidirectional — periodontal inflammation makes blood sugar harder to control and vice versa.
- Reporting changes early. Bleeding, swelling or discomfort at any point, not at the next appointment.

Why This Is A Periodontist’s Question
Periodontists are dental implant specialists as much as gum specialists: three years of training after dental school, entirely on the gum tissue and bone that support teeth, and on dental implant placement into them. Gum disease is the condition the specialty exists for.
Where implants are being planned for a mouth with periodontal disease, the two decisions are one decision. How aggressively to treat the disease, which teeth to keep, where bone will be adequate, whether to graft or work around the loss, and when the mouth is genuinely stable enough to proceed — those judgements depend on each other. Splitting them between a practice that treats the gums and another that places the dental implants introduces a seam exactly where the case is most likely to fail.
Our periodontists have placed over 10,000 implants and completed more than 1,000 full-arch cases, a large share of them for patients who were told elsewhere that gum disease had ruled implants out.
Frequently Asked Questions About Gum Disease And Implants
Can someone with periodontal disease get dental implants? Yes, once the disease is treated and stable. Having had periodontal disease is not a barrier. Having it active and untreated at the time of placement is.
Can I get dental implants if I have gum disease right now? Not while it is active. Untreated periodontal disease is the one thing that rules placement out on the day, and the most common reason people are told they cannot have dental implants is gum disease. Treat it and the answer usually changes.
Do I still qualify for dental implants if I have already lost bone? Usually. Bone loss changes how the case is planned rather than whether it can be done, and many patients get dental implants even after severe disease. Gum disease often takes more bone than people realise, which is why the scan matters.
Will I need a bone or gum graft? Sometimes one, sometimes both, sometimes neither. Periodontal disease may have thinned the soft tissue as well as the bone, and both are assessed together.
Can I get dental implants with bad gums? Almost certainly, after treatment. “Bad gums” covers everything from mild gingivitis to advanced bone loss, and the plan differs enormously between them. An assessment tells you which you have.
Do dental implants fail more often in patients who have had gum disease? Success rates are slightly lower than in patients with no periodontal history, but still high — and the gap narrows sharply with proper treatment beforehand and a maintenance schedule afterwards.
Will I need a bone graft? Often, though not always, and rarely as much as patients fear. A CBCT scan is the only way to know. Where extensive grafting would be needed, alternatives that use the bone you still have are frequently available.
Can I keep some natural teeth and have implants for the rest? Yes, and this is common. The question is whether each remaining tooth has enough support to last, because a failing tooth next to an implant puts that implant at risk.
How much does it cost to treat gum disease before implants? It depends entirely on severity, from a course of scaling and root planing to surgical treatment across multiple areas. We give you an exact figure after assessment, and check what your insurance covers — periodontal treatment is often covered where implants are not.
Is it too late if I have already lost several teeth? No. Patients who have lost teeth to periodontal disease are among the most common cases we treat, and full-arch options exist even where bone loss is advanced.
Find Out Where You Actually Stand
If gum disease has cost you teeth, or you are considering implants and have been told your gums rule them out, a consultation with one of our board-certified periodontists will tell you what is realistic. We measure the disease, scan the bone, and set out what treatment would involve and how long it would take before implants become possible.
Call (347) 493-2439 or book your consultation online. We see patients in Manhattan, Nutley, Long Island and Westchester.
